What Is VATS? What Are the Advantages of Minimally Invasive Thoracic Surgery?
19/10/2026
Does Pectus Excavatum Affect the Heart and Lungs?
19/10/2026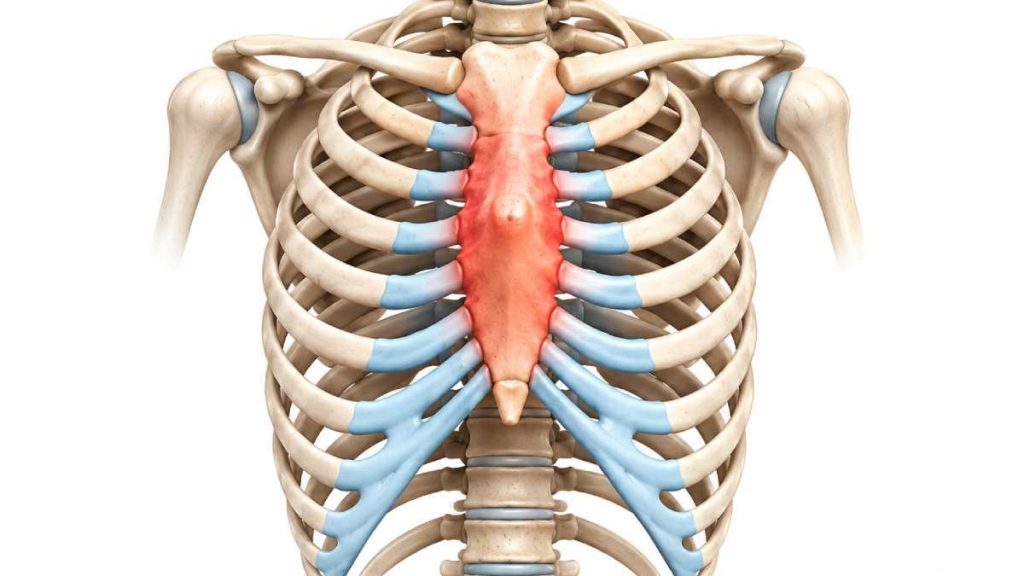
Pectus carinatum is a chest wall deformity in which the breastbone and part of the rib cage project forward. It is also commonly known as “pigeon chest.”
In children and adolescents whose chest wall is still flexible, brace treatment may be considered as a non-surgical treatment option.
The main principle of bracing is to apply controlled and continuous pressure to the protruding part of the chest wall, gradually guiding it toward a more natural contour over time.
However, not every patient with pectus carinatum is suitable for brace treatment. The type of deformity, flexibility of the chest wall, age, growth stage, and ability to use the brace consistently all influence treatment planning.
What Is Pectus Carinatum?
Pectus carinatum is a chest wall deformity in which the sternum and adjacent costal cartilages project forward.
The deformity may be:
- central,
- more prominent on one side,
- bilateral,
- symmetrical,
- asymmetrical.
In some patients, the protrusion is mild and noticed mainly because of appearance. In others, the deformity may be more pronounced.
Pectus carinatum often becomes more noticeable during periods of rapid growth, particularly during adolescence.
What Is a Pectus Carinatum Brace?
A pectus carinatum brace is a specially designed orthotic device used to apply controlled pressure to the most prominent area of the chest.
Unlike braces used mainly for spinal conditions, the purpose here is not to correct the spine but to reshape the chest wall gradually.
The brace is generally adjusted according to the patient’s individual chest shape.
A pressure pad is positioned over the area of greatest prominence, while the back and side supports help distribute the corrective force in a controlled manner.
How Does Pectus Carinatum Bracing Work?
The chest wall of children and adolescents is generally more flexible than that of adults.
During growth, the costal cartilages and chest wall continue to develop and can be more responsive to external pressure.
Brace treatment makes use of this flexibility.
By applying regular, controlled pressure to the protruding area, the aim is to gradually guide the chest wall toward a flatter and more balanced contour.
This process usually occurs over months rather than after a single adjustment or short period of use.
Who Is Suitable for Pectus Carinatum Brace Treatment?
Suitability for bracing is assessed individually.
Brace treatment may be considered particularly in patients who:
- have a flexible chest wall,
- are still growing,
- have a deformity that can be corrected with external pressure,
- are able to follow a regular brace-wearing schedule.
Age alone does not determine suitability.
Two patients of the same age may have very different chest wall flexibility.
For this reason, the degree to which the protrusion can be corrected with manual pressure is an important part of clinical assessment.
What Is the Best Age for Pectus Carinatum Bracing?
One of the most important factors is chest wall flexibility.
For this reason, childhood and adolescence are often the periods in which brace treatment can be more effective.
Pectus carinatum frequently becomes more visible during the adolescent growth spurt, while the chest wall is still relatively malleable.
However, there is no single age cut-off that applies to everyone.
Treatment planning is based more on:
- chest wall flexibility,
- severity of the deformity,
- growth stage,
- expected treatment compliance.
Can Adults Use a Pectus Carinatum Brace?
In adults, the chest wall is usually less flexible than in children or adolescents.
As a result, the potential for reshaping the chest wall with a brace may be more limited.
However, some young adults may still have sufficient chest wall flexibility for brace treatment to be considered.
In older patients or in those with a rigid chest wall, the expected response to bracing may be lower.
For this reason, brace treatment in adults should be assessed individually.
What Happens Before Starting Brace Treatment?
Before treatment begins, the chest wall is assessed in detail.
The examination may include evaluation of:
- type of deformity,
- exact location of the protrusion,
- whether it is symmetrical or asymmetrical,
- flexibility of the chest wall,
- how much the deformity corrects with pressure,
- associated posture or spinal problems.
Additional imaging or other tests may be required in selected patients.
However, CT scanning is not necessary in every patient with pectus carinatum.
Tests are selected according to the clinical findings.
Is the Brace Custom-Made?
Pectus carinatum varies in shape and location from one patient to another.
For this reason, the brace needs to fit the individual chest wall appropriately.
Brace settings may be adjusted according to:
- location of the protrusion,
- chest circumference,
- required pressure,
- growth of the patient.
In growing children and adolescents, body measurements may change over time, so the brace may need repeated adjustments during follow-up.
What Is a Dynamic Compression Brace?
A dynamic compression brace is one of the systems used in pectus carinatum treatment.
Its purpose is to apply and adjust pressure in a controlled manner.
Too little pressure may not provide enough corrective effect, while excessive pressure may cause:
- pain,
- skin irritation,
- redness,
- poor tolerance of the brace.
The goal is therefore not to apply the maximum possible pressure, but an effective level of pressure that can be tolerated safely.
How Many Hours a Day Should a Pectus Carinatum Brace Be Worn?
The number of hours per day depends on the deformity, treatment phase, brace system, and individual response.
In some treatment programs, the brace may be worn for much of the day during the initial correction phase.
As the chest contour improves, the wearing time may be reduced and the patient may enter a maintenance phase.
There is no single daily wearing schedule that is appropriate for every patient.
Treatment is adjusted according to:
- chest wall flexibility,
- speed of correction,
- skin tolerance,
- daily routine,
- patient compliance.
Is the Brace Worn at Night?
Depending on the treatment plan, the brace may also be worn during sleep.
For patients who require extended daily use, nighttime wear may form part of the schedule.
However, whether nighttime use is appropriate depends on the brace type, applied pressure, and patient tolerance.
If the brace causes significant pain, excessive pressure, or skin problems, its fit and settings should be reassessed.
How Long Does Pectus Carinatum Brace Treatment Take?
Treatment duration varies considerably between patients.
Some patients may notice an early improvement within the first few months, while treatment may need to continue for a longer period to maintain the correction.
The overall duration depends on:
- severity of the deformity,
- flexibility of the chest wall,
- age,
- growth rate,
- consistency of brace use,
- stability of the achieved correction.
Treatment is not necessarily complete when the protrusion first appears improved.
A maintenance phase may be required to help preserve the corrected chest contour.
When Can Results Be Seen?
Some patients may notice changes in chest shape during the early months of treatment.
However, early improvement does not mean treatment should immediately be stopped.
The chest wall often needs continued support for the new shape to become more stable.
Stopping treatment too early may increase the risk of recurrence.
Does Pectus Carinatum Bracing Really Work?
In appropriately selected patients, regular brace treatment can be an effective non-surgical option.
Factors associated with better treatment response include:
- good chest wall flexibility,
- suitable deformity type,
- younger age or ongoing growth,
- proper brace adjustment,
- consistent daily use,
- regular follow-up.
If the brace is worn only occasionally or the planned treatment schedule cannot be maintained, the degree of correction may be more limited.
Why Is Patient Compliance So Important?
Brace treatment is not a one-time procedure.
Its effect depends heavily on regular use over weeks and months.
For adolescents in particular, compliance may be affected by:
- visibility of the brace under clothing,
- discomfort in warm weather,
- school or sports activities,
- skin sensitivity,
- concerns about appearance.
For this reason, a treatment plan should be realistic enough to fit into the patient’s daily routine.
Can You Exercise While Wearing a Pectus Carinatum Brace?
Most patients with pectus carinatum do not need to avoid physical activity completely.
The brace may be removed for some sports or exercise sessions and then reapplied afterwards.
Recommendations may differ for contact sports, intense training, or individual clinical situations.
Exercise planning should therefore be adapted to the patient.
Can Exercise Correct Pectus Carinatum?
Exercise may help:
- strengthen the back and shoulder muscles,
- improve posture,
- improve overall chest appearance,
- support physical conditioning.
However, a structural pectus carinatum deformity is not generally expected to disappear through exercise alone.
Exercise may be used as a supportive measure alongside brace treatment in selected patients.
Is Pectus Carinatum Bracing Painful?
A certain amount of pressure and tightness may be expected.
Significant pain, however, should not be considered normal.
Excessive pressure may cause:
- pain,
- numbness,
- skin breakdown,
- persistent redness,
- breathing discomfort.
If these occur, the brace settings should be reassessed.
Can a Pectus Carinatum Brace Cause Skin Marks?
Temporary redness may occur where the brace contacts the skin.
However, persistent redness, sores, or significant irritation may indicate excessive pressure or poor brace fit.
Regular skin checks are therefore important.
Sweating and friction during warm weather may also increase the risk of skin irritation.
Why Are Follow-Up Appointments Important?
Brace treatment is not completed simply by providing the device.
During follow-up, the clinician may assess:
- changes in chest contour,
- pressure applied by the brace,
- growth of the patient,
- fit of the brace,
- skin condition,
- daily wearing time.
The brace may need to be adjusted repeatedly during treatment.
This is particularly important during periods of rapid growth.
Can Pectus Carinatum Return After Brace Treatment?
Recurrence is possible.
The risk may be higher if treatment is stopped too early or if the maintenance phase is not completed while the patient is still growing.
For this reason, some patients may need a period of reduced-intensity brace use after the main correction phase.
The length of maintenance depends on age, growth, and the characteristics of the deformity.
When May Brace Treatment Be Less Effective?
Brace treatment may provide limited correction in some patients.
Possible reasons include:
- rigid chest wall,
- older age,
- severe or complex deformity,
- certain asymmetrical forms,
- inconsistent brace use,
- poor treatment compliance.
In these situations, other treatment options may need to be considered.
When Is Surgery Considered for Pectus Carinatum?
Because brace treatment is an important non-surgical option, surgery is not required for every patient.
Surgery may be considered in selected situations such as:
- a chest wall that is too rigid for bracing,
- insufficient response despite appropriate brace treatment,
- anatomy that is not suitable for bracing,
- severe or complex deformity.
The decision is based on the structure of the deformity and the patient’s overall situation rather than appearance alone.
Brace or Surgery: Which Is Better for Pectus Carinatum?
These options are not interchangeable for every patient.
In many growing patients with a flexible chest wall, brace treatment may be considered first.
In patients with a rigid chest wall, severe deformity, or poor response to bracing, surgery may become an option.
The key question is therefore not “Which treatment is better?” but “Which treatment is more appropriate for this patient?”
What Factors Affect the Success of Brace Treatment?
The outcome of treatment depends on several factors.
Important elements include:
- appropriate patient selection,
- sufficient chest wall flexibility,
- correct brace pressure,
- consistent use,
- regular follow-up,
- monitoring during growth,
- continuation of the maintenance phase when needed.
For this reason, pectus carinatum brace treatment is not simply the use of a device but a structured treatment process requiring follow-up over time.
Frequently Asked Questions
1. What is a pectus carinatum brace?
It is a specially designed orthotic device that applies controlled pressure to the protruding area of the chest wall to gradually improve its contour.
2. Can pectus carinatum be corrected with a brace?
In suitable patients with a flexible chest wall and good treatment compliance, brace treatment can provide meaningful correction.
3. What age is best for pectus carinatum bracing?
There is no single age limit. Chest wall flexibility and growth stage are more important than chronological age. Bracing is commonly considered during childhood and adolescence.
4. How many hours a day should the brace be worn?
Daily wearing time varies by patient and treatment phase. Some programs require extended wear during the initial correction phase, followed by reduced use later.
5. How many months does pectus carinatum brace treatment take?
There is no fixed duration. Treatment may last several months or longer depending on severity, flexibility, growth, and consistency of use.
6. Should the brace be worn at night?
Nighttime use may be included in some treatment schedules. The exact plan depends on brace type, pressure settings, and patient tolerance.
7. Is wearing a pectus carinatum brace painful?
Pressure is expected, but significant pain is not. Persistent pain or skin irritation may indicate that the brace requires adjustment.
8. Can adults benefit from pectus carinatum bracing?
Some young adults with sufficient chest wall flexibility may still be considered for bracing, although the response may be more limited than in younger patients.
9. Can pectus carinatum return after brace treatment?
Yes. Recurrence can occur, particularly if treatment is stopped early or the maintenance phase is not completed during ongoing growth.
10. Is a brace or surgery better for pectus carinatum?
The appropriate treatment depends on the individual patient. Bracing may be preferred in flexible deformities, while surgery may be considered in selected rigid, severe, or brace-resistant cases.
Information Note:
This content is intended for general informational purposes only. Suitability for pectus carinatum brace treatment depends on the type and severity of the deformity, chest wall flexibility, age, growth stage, and treatment compliance. The required pressure, daily wearing time, and overall treatment duration are not the same for every patient. The information provided here does not replace individual medical assessment, diagnosis, or treatment planning.